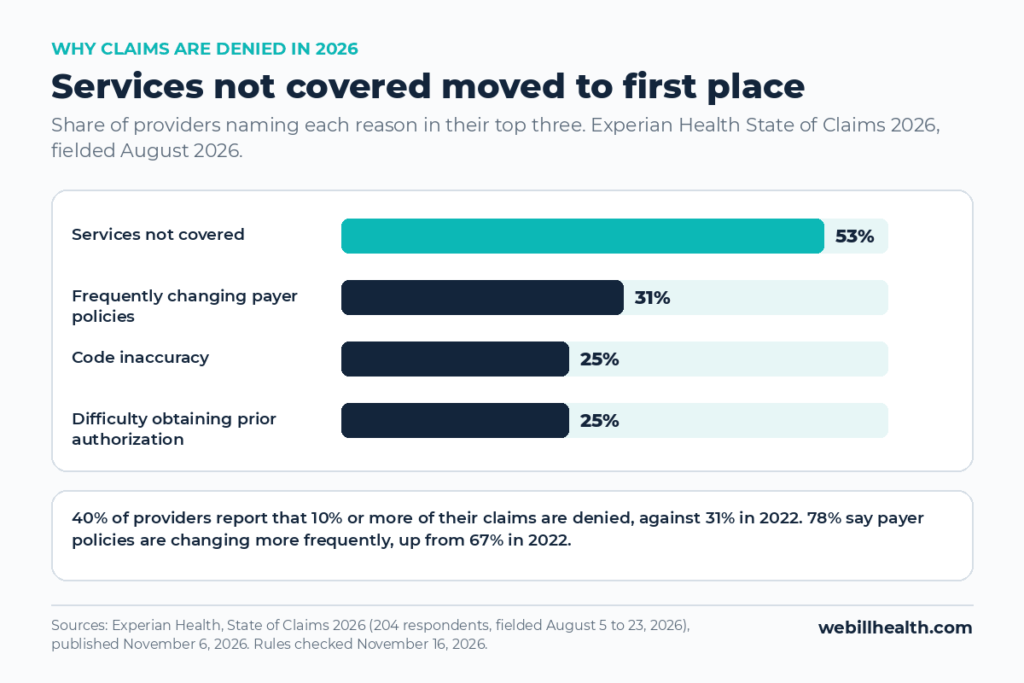
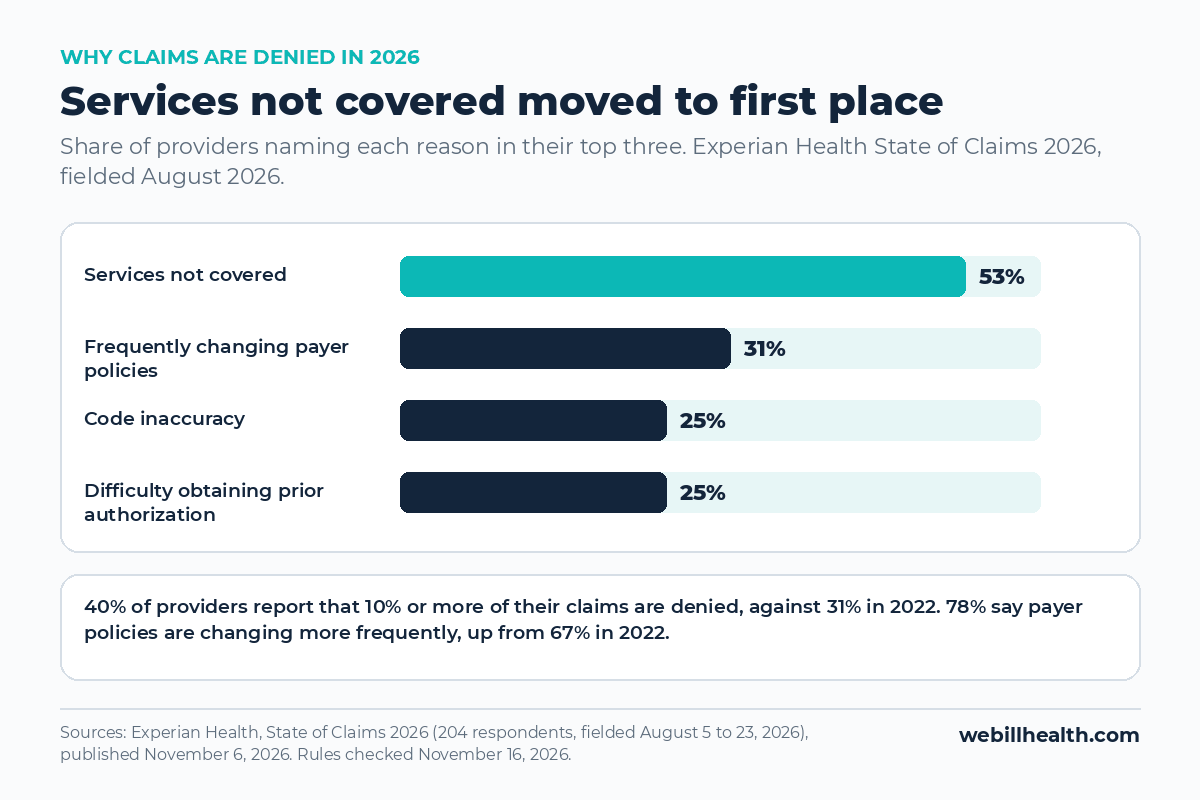
Most medical claims are denied for a short list of preventable reasons: services the plan does not cover, missing or wrong patient data, missing prior authorization, coding and modifier errors, and late filing. In Experian Health’s State of Claims 2026 survey, “services not covered” became the top reason for the first time. MGMA puts the typical practice denial rate at 7% to 8%.
Updated November 16, 2026
How common are claim denials in 2026?
About one claim in ten is denied on first submission across all payers. Kodiak Solutions measured a 10.63% initial denial rate in the first half of 2026, and MGMA puts the typical medical practice at 7% to 8%, with well run practices under 5%.
| Measure | Figure | Source |
|---|---|---|
| Initial denial rate, all payers, first half 2026 | 10.63% | Kodiak Solutions |
| Typical first submission denial rate, medical practices | 7% to 8% | MGMA, July 2026 |
| Best practice denial rate | Under 5% | MGMA, July 2026 |
| Providers with 10% or more of claims denied | 40% in 2026, against 31% in 2022 | Experian Health, State of Claims 2026 |
| Takebacks after payment, first half 2026 | 1.57% of net revenue | Kodiak Solutions via TechTarget, September 2026 |
The takeback figure matters. Payers are denying slightly fewer claims up front and recovering more money after payment, so a clean remittance is no longer the end of the story. Our 2026 denial benchmarks white paper has the full data.
Why are claim denials increasing in healthcare in 2026?
Denials stay high in 2026 because payer rules change faster than practices can track them. In Experian Health’s State of Claims 2026 survey, 78% of providers said payer policies are changing more frequently, up from 67% in 2022, and “services not covered” became the top denial reason.
The money lost is also shifting toward clinical denials. Kodiak Solutions found providers lost more than $48 billion in 2025 to final denials and uncollected patient amounts, up from $38.6 billion in 2024, with prior authorization and medical necessity denials driving nearly all of the increase.
What are the most common reasons claims are denied?
Every denial carries a Claim Adjustment Reason Code (CARC) on the remittance. These codes cover the most common preventable denials and where each one starts.
| Denial reason | Common CARC | Where it starts | How to prevent it |
|---|---|---|---|
| Patient not covered on the date of service | 27 | Front desk | Verify eligibility before every visit, including returning patients |
| Missing or incomplete information | 16 | Registration or coding | Check demographics, member ID and required fields before submission |
| Prior authorization missing | 197 | Scheduling | Check authorization rules by plan and service before scheduling |
| Not medically necessary for the diagnosis | 50 | Documentation and coding | Match diagnosis codes to the payer’s coverage policy |
| Not covered under the benefit plan | 96 | Benefits check | Confirm the service is a covered benefit as well as that the patient is active |
| Service bundled into another service | 97 | Coding | Check NCCI edits and use modifiers only when documentation supports them |
| Duplicate claim | 18 | Billing workflow | Check claim status before resubmitting |
| Filing deadline passed | 29 | Billing workflow | Submit promptly and track each payer’s timely filing limit |
For referral and authorization codes in detail, see referral and authorization denials.
Are there common documentation errors that lead to denied claims in 2026?
Yes. In Experian Health’s Claim Denial Management survey of 210 revenue cycle leaders in January and February 2026, missing or incomplete documentation was the most preventable cause of denials at 53%, ahead of coding errors at 45% and duplicate claims at 39%.
The documentation errors that cost the most are clinical. A note that records the visit without stating why the service was necessary fails a medical necessity review, an E/M billed with Modifier 25 without a separate problem in the note fails review, and an authorization that names a different code, unit or site than the one performed denies as a mismatch.
What should billing teams compare when evaluating insurer denial rates?
Compare insurers on the same measure: denials on first adjudication divided by claims adjudicated in the same period, counted by claim and by dollars. Then split each payer by CPT family and by CARC, so a payer that denies one service line heavily does not hide inside a blended rate.
Public data helps as a benchmark. KFF found Medicare Advantage insurers denied 7.7% of prior authorization requests in 2024, and since 2026 Medicare Advantage, Medicaid and CHIP plans covered by CMS-0057-F publish their own prior authorization approval and timing metrics every March 31.
Which denials grow in 2027?
Several changes on January 1, 2027 will create new denials for practices that are not ready. Each one has its own page.
- CPT 2027 adds, deletes and revises codes, and claims with deleted codes deny. See CPT 2027 changes for small practices.
- Payers covered by CMS-0057-F must run electronic prior authorization APIs by January 1, 2027. See prior authorization changes in 2027.
- Medicare Advantage plan exits move patients to new plans, and providers not enrolled with the new plan see out of network denials.
- Payer downcoding of level 4 and 5 E/M visits continues. See BCBS downcoding by state.
- Medicare pays the lower service at 80% when an office E/M with Modifier 25 falls on the same day as a 0 day global procedure. See the 2027 Modifier 25 payment cut.
How do you reduce claim denials in a small practice?
Find the three causes that repeat in your own claims and close each one at the step that creates it. Run these steps in order.
- Measure your denial rate the way benchmarks do, and track clearinghouse rejections separately.
- Split the last 90 days of denials by payer, CPT family and CARC, and find your top three causes.
- Verify eligibility and covered benefits before every visit, including returning patients.
- Build an authorization list by payer and service, and check it at scheduling.
- Review every claim before submission against the payer’s rules for your specialty, including modifiers and NCCI edits.
- Track credentialing and CAQH attestation dates for every provider.
- Work every denial within days, because payers set appeal deadlines and waiting turns denials into write offs.
How can outsourced billing reduce a claims denial rate?
Outsourced billing reduces denials when the partner reviews every claim against payer rules for your specialty before submission and fixes the cause behind each denial as well as the claim itself. Ask any partner to report denials by payer, CPT family and CARC every week, so you can see whether the top causes are shrinking.
Outsourcing does not fix the front desk on its own. Eligibility, benefits and authorization checks still start at scheduling, so the partner needs a defined handoff with your staff or should run those checks itself.
What should a denial management service include in 2026?
A denial management service in 2026 should cover prevention, follow up and reporting together. Look for pre submission review against payer and specialty rules, eligibility and authorization checks before the visit, denial work within days, appeals built on the payer’s stated reason, and weekly reporting by payer and CARC.
It should also track takebacks after payment, because Kodiak Solutions found payers recovering 1.57% of net revenue after payment in the first half of 2026.
Should you appeal denied claims?
Yes, when the denial is wrong and the documentation supports the claim. KFF found that 80.7% of Medicare Advantage prior authorization denials that were appealed in 2024 were overturned in whole or in part, yet only 11.5% were appealed.
An appeal should answer the payer’s specific denial reason with the documentation that disproves it. Since January 1, 2026, plans covered by CMS-0057-F must give a specific reason for every prior authorization denial, which makes that answer easier to build.
Frequently asked questions
What is the most common reason medical claims are denied in 2026?
Services not covered. In Experian Health’s State of Claims 2026 survey, 53% of providers placed it in their top three denial reasons, the first time it has ranked first since the survey began in 2022.
What is a good denial rate for a medical practice?
MGMA puts the typical first submission denial rate for medical practices at 7% to 8%, and well run practices get under 5%. Measure it by claims and by dollars, and leave clearinghouse rejections out.
What is the difference between a rejection and a denial?
A rejection is returned before the payer processes the claim, usually by the clearinghouse for a format or data error, and can be corrected and resent. A denial is a payer decision after processing and needs a corrected claim or an appeal.
How long do I have to appeal a denied Medicare claim?
A Medicare first level redetermination must be filed within 120 days of receiving the initial determination, under 42 CFR 405.942. Commercial and Medicare Advantage deadlines are set by the plan and the contract.
WeBill Health take
WeBill Health maintains internal payer rule libraries organized by specialty and by carrier, spanning more than 500 payer rulesets, built and updated by people who work claims in your specialty every day. Every claim receives human pre submission review against them before it goes out, and that review stands behind a 98% clean claim rate and a 48 hour submission guarantee. See how denials are traced to their cause in Denial Defense 2.0.
Request a Revenue Defense Audit to see your top three denial causes by payer, code and reason.
Sources
- Experian Health, State of Claims 2026, November 6, 2026
- Medical Economics, services not covered now tops the denial list, State of Claims 2026 findings (November 2026)
- Experian Health, Claim Denial Management survey results, April 7, 2026
- MGMA Stat, days in A/R and payer pressure in 2026 (July 2026)
- Kodiak Solutions via Business Wire, 2025 denial and lost revenue data, March 31, 2026
- TechTarget on Kodiak Solutions first half 2026 takeback data, September 2026
- KFF, Medicare Advantage insurers made nearly 53 million prior authorization determinations in 2024, January 28, 2026
- CMS, Interoperability and Prior Authorization Final Rule CMS-0057-F, page last modified October 8, 2026
- eCFR, 42 CFR 405.942, redetermination filing deadline, current text
- X12, Claim Adjustment Reason Codes, list status reviewed November 1, 2026