Update, November 6, 2026: CMS finalized the CY 2027 Physician Fee Schedule on November 4. The conversion factor for most clinicians is $32.63, and the same day cut was finalized at 20 percent, so Medicare pays the second service at 80 percent and only when the procedure carries a zero day global period. See what the final rule changes for small practices.
Dermatology claims going into 2027 are denied mostly for documentation and coding reasons that payers can check line by line. The common ones are same day E/M visits billed with modifier 25 next to a minor procedure, multiple lesion claims missing modifier 59 or XS, destruction and excision codes reported for the same lesion, thin Mohs notes, biopsy codes reported out of sequence, and benign lesion removals that read as cosmetic. Biologics prior authorization and new Medicare skin substitute rules add a second layer. Each can be fixed in the chart before the claim goes out.
What changed for dermatology billing between 2026 and 2027?
Four federal items shape dermatology revenue right now. Three are now final and one was withdrawn.
| Change | Status | What it means for a dermatology practice |
|---|---|---|
| Same day E/M with a zero day global procedure paid at 80% | Finalized in the CY2027 Physician Fee Schedule (November 4, 2026) | Medicare pays the higher valued service in full and the other at 80%, starting January 1, 2027. CMS dropped 10 and 90 day globals from the policy |
| Skin substitutes paid as incident to supplies | Final for CY2026 | A single rate of approximately $127.28 per square centimeter before geographic adjustment, in the office and hospital outpatient settings |
| New skin substitute LCDs for diabetic foot and venous leg ulcers | Withdrawn December 24, 2025, before their January 1, 2026 start | Existing Novitas, CGS and First Coast policies stay in force |
| WISeR prior authorization model in Original Medicare | Live since January 1, 2026, through 2031 | Skin and tissue substitutes are included only where an active LCD exists |
Why does modifier 25 cause so many dermatology denials?
The HHS Office of Inspector General found that in 2019 and 2020, about 61.5 percent of Medicare paid dermatology E/M claims included a same day minor surgical procedure by the same dermatologist.
The rule behind the denials sits in the NCCI Policy Manual. The decision to perform a minor surgical procedure is included in the payment for that procedure. A separate E/M is payable only when it is significant, separately identifiable and unrelated to the decision to do the procedure, and it must carry modifier 25.
A note that reads “lesion on back, shave biopsy performed” supports the biopsy and nothing else. A note that also documents management of the patient’s psoriasis and a medication change gives the E/M its own problem in the assessment and plan.
OIG reviewed 100 sampled dermatology E/M services billed with same day minor procedures and found 90 met Medicare requirements. The 10 that failed led OIG to estimate $62,915,655 in overpayments, and CMS committed to continued claim reviews and education on modifier 25.
Will Medicare pay a same day E/M at 50% in 2027?
No. The CY2027 final rule, released November 4, 2026, pays the higher valued service in full and the other at 80% when a separately identifiable office or outpatient E/M visit happens on the same day as a zero day global procedure. CMS first proposed 50% and a wider scope.
CMS posted the final rule (CMS 1848 F) on November 4, 2026. A Milliman analysis estimates dermatology would take the largest reduction of any specialty in absolute dollars, about $291 million, or roughly 6.1% of the specialty’s total Part B allowed amount.
Even if it is finalized, documentation still decides whether the E/M is paid at all. Our full analysis of the proposal is in CMS modifier 25 payment cut 2027.
How should multiple lesions be coded with modifier 59 or XS?
The NCCI manual allows multiple removal codes on the same day when they are on different sites or lesions, reported with anatomic modifiers or modifier 59 or XS. Only one removal code may be reported for a single lesion.
CMS guidance from April 2026 (MLN1783722) gives a dermatology example. A skin biopsy (11102) and destruction of premalignant lesions (17000) on different anatomic sites on the same side of the body can take modifier 59 or XS. When the two procedures are on opposite sides, use RT and LT instead. CMS also says to use modifier 59 only when no other modifier better describes the relationship.
A body map or numbered lesion list with site, size and method for each lesion lets the payer match every code to a lesion.
Should a lesion be coded as destruction or excision?
These are separate code families, and payers deny claims that report both for the same lesion. The NCCI manual says that when a removal starts with one method and converts to another, only the code for the completed procedure is reported.
| Code range | Service | How it is counted |
|---|---|---|
| 17000, 17003, 17004 | Destruction of premalignant lesions such as actinic keratoses | 17000 for the first lesion, 17003 for each additional lesion up to 14, one unit of 17004 for 15 or more |
| 17110, 17111 | Destruction of benign lesions | 17110 for up to 14 lesions, 17111 for 15 or more, each billed as one unit |
| 11400 to 11646 | Excision of benign and malignant lesions | By site and excised diameter, which is the largest lesion diameter plus twice the narrowest margin |
If the note records only the lesion size and leaves out the margin, the excision cannot be sized correctly.
What do Medicare contractors require in a Mohs surgery note?
CGS billing article A56836, revised effective May 7, 2026, lays out what auditors expect for Mohs codes 17311 to 17315. The operative and pathology records must show accepted Mohs technique, with one physician performing both the surgery and the pathology. The notes should record the lesion’s location, number and size, the number of stages, and the number of specimens per stage. The record should also state why Mohs was chosen, based on the lesion’s complexity, size or location.
Code selection follows anatomy. Codes 17311 and 17312 cover the head, neck, hands, feet, genitalia, and sites where surgery directly involves muscle, cartilage, bone, tendon, major nerves or vessels. Codes 17313 and 17314 cover the trunk, arms and legs.
Two NCCI rules cause most Mohs denials. Pathology codes 88300 to 88309 and 88329 to 88332 are included in Mohs and should not be billed with it. Repairs, grafts and flaps are separately reportable. A same day diagnostic biopsy before Mohs can be reported with modifier 59, XS or XU, and CGS expects the chart to show either that no biopsy of that lesion was done in the prior 60 days or that recent results could not be obtained.
How should biopsy codes 11102 to 11107 be reported?
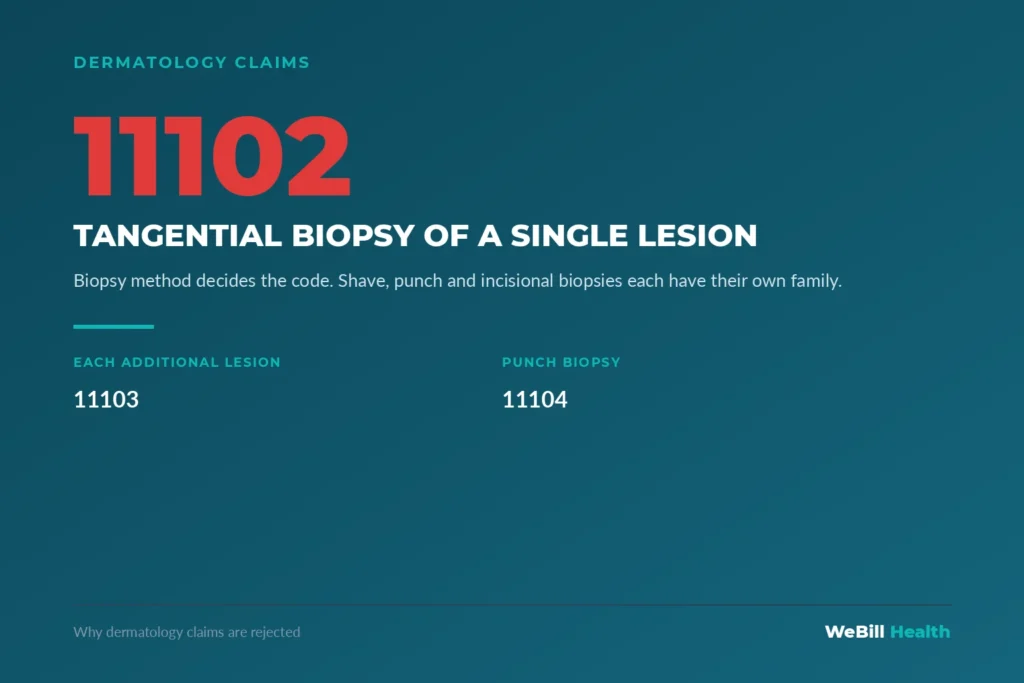
Biopsy codes are split by technique, with a primary code for the first lesion and an add on code for each additional one.
| Technique | Primary code | Add on code |
|---|---|---|
| Tangential | 11102 | 11103 |
| Punch | 11104 | 11105 |
| Incisional | 11106 | 11107 |
When more than one technique is used on the same day, report only one primary code, the one with the highest RVUs, and use the add on codes that match the other techniques. Billing two primary codes is a common edit failure.
The NCCI manual adds that a biopsy of the same lesion that is removed at the same encounter is not separately reported. A biopsy of a different lesion can be reported with the removal code when the chart shows it was a different lesion.
When is lesion removal cosmetic in Medicare’s eyes?
The Novitas LCD for Removal of Benign Skin Lesions (L34938) treats removal of benign lesions that pose no threat to health or function as cosmetic and not covered. Removal of seborrheic keratoses, cysts, nevi and similar lesions is covered when the record clearly documents at least one indication. These include a lesion that is symptomatic, has changed in appearance, or shows inflammation or infection, along with obstruction of an orifice, restricted eye function, uncertain diagnosis with concern for malignancy, prior biopsy suggesting atypia, documented recurrent trauma, and an epidermal or pilar cyst with a history of infection, drainage or rupture.
The LCD is explicit that phrases like “irritated skin lesion” or “inflamed seborrheic keratosis” are not enough alone. The note needs the actual signs, symptoms and findings. A lesion’s location alone does not make it covered. When a patient chooses removal for cosmetic reasons, the patient is responsible for the cost, provided the practice told them in advance that Medicare would not pay.
What changed for skin substitutes in 2026?
The CY2026 Physician Fee Schedule final rule moved most skin substitute products to payment as incident to supplies when used in a covered application procedure, at a single rate of approximately $127.28 per square centimeter.
The new LCDs for diabetic foot ulcers and venous leg ulcers were withdrawn by the MACs on December 24, 2025, days before their January 1, 2026 start. The older Novitas, CGS and First Coast skin substitute policies remain in effect.
WISeR adds prior authorization or pre payment review for selected services in Original Medicare in New Jersey, Ohio, Oklahoma, Texas, Arizona and Washington. Skin and tissue substitutes are included only in WISeR states with an active skin substitute LCD, which leaves New Jersey, Ohio, Oklahoma and Texas. Skipping the request sends the claim to pre payment medical review. See our WISeR prior authorization study.
Why do biologics prior authorizations fail?
The AAD calls prior authorization one of the top administrative burdens dermatologists face, and it offers members an appeal letter tool and a state map of step therapy laws. For biologics, a request that does not line up with the payer’s written criteria for that drug is the usual starting point for a denial.
The CMS Interoperability and Prior Authorization final rule requires Medicare Advantage, Medicaid, CHIP and other impacted payers to decide within 72 hours for urgent requests and seven calendar days for standard requests, starting January 1, 2026, with a specific reason for every denial. That rule does not apply to drugs. A separate CMS proposal from 2026 would extend similar requirements to drugs, including a specific denial reason, with a proposed compliance date of October 1, 2027. It is still a proposal.
Until then, the payer’s own policy governs, so prior treatments, dates and outcomes belong in one place in the chart. More detail is in our guide to prior authorization changes in 2027.
How WeBill Health handles dermatology claim denials
WeBill Health works dermatology denials at the root cause, usually the note, the modifier or the code pairing. WeBill Health maintains internal payer rule libraries organized by specialty and by carrier, built and updated by experts who work claims in your specialty every day. Every claim receives human pre submission review against them before it goes out, across more than 500 payer rulesets.
For dermatology, that review covers modifier 25 support, lesion mapping for 59 and XS, excision size with margins, Mohs stage counts, biopsy sequencing and medical necessity language for benign lesions. As your partner, WeBill Health holds a 98% clean claim rate and a 48 hour submission guarantee, and defends denied claims with appeals built on the payer’s own policy language.
Is modifier 25 or lesion coding costing you payments? Request your Revenue Defense Audit and we will review your same day E/M claims, lesion and Mohs coding, biopsy sequencing and recent denials by payer. For a quick read first, get your Revenue Defense Score in 60 seconds.
Frequently asked questions
Is the 50% same day E/M payment cut final for 2027?
No. As of October 29, 2026, CMS has posted only the proposed CY2027 Physician Fee Schedule rule. The AMA expects the final rule by November 1, with changes taking effect January 1, 2027 if finalized.
Does OIG think dermatologists overuse modifier 25?
OIG’s November 2025 audit found that 90 of 100 sampled dermatology E/M services billed with a same day minor procedure met Medicare requirements. OIG still recommended continued claim reviews and education, so documentation for the separate visit matters.
Can I bill a biopsy and a destruction on the same day?
Yes, when they are on different lesions or different sites. Use modifier XS or 59 on the same side of the body, or RT and LT on opposite sides, and document each lesion separately.
Are skin substitutes subject to Medicare prior authorization?
Only in WISeR states with an active skin substitute LCD, which currently means New Jersey, Ohio, Oklahoma and Texas in Original Medicare. Medicare Advantage plans set their own rules.
Sources
- Calendar Year 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet, CMS
- Physician Fee Schedule Federal Regulation Notices, CMS
- 2027 proposed Medicare fee schedule: What physicians need to know, AMA
- CY 2027 MPFS proposed modifier 25 policy impact, Milliman
- Dermatology Providers Generally Met Medicare Requirements for Evaluation and Management Services Performed on Same Day as Minor Surgical Procedures, HHS OIG
- OIG report supports dermatologists’ use of modifier 25, AAD
- Medicare NCCI Policy Manual 2026, Chapter 3, Integumentary System, CMS
- Proper Use of Modifiers 59, XE, XP, XS and XU (MLN1783722), CMS
- Skin Deep: How to Properly Code for Biopsies and Lesion Removal, AAFP Family Practice Management
- Billing and Coding: Mohs Micrographic Surgery (A56836), CGS
- Removal of Benign Skin Lesions (L34938), Novitas
- Calendar Year 2026 Medicare Physician Fee Schedule Final Rule fact sheet, CMS
- CMS reclassifies certain skin substitutes and cuts payment under the MPFS, Reed Smith
- Upcoming update on final LCDs for certain skin substitutes, CMS
- Medicare Part B MACs withdraw skin substitute LCDs, what we know and what remains unclear, HMP Wounds
- CMS withdraws skin substitute LCDs scheduled for 2026, APMA
- WISeR Model Frequently Asked Questions, CMS
- CMS Interoperability and Prior Authorization Final Rule fact sheet, CMS
- Interoperability Standards and Prior Authorization for Drugs proposed rule briefing slides, CMS
- Prior Authorization Assistance Learning Center, AAD